
Phone
0772-443572
mcmcblessed@gmail.com
Location
Nshozi, Mazinga Ward, Bushenyi
The First Community General Hospital in Greater Bushenyi
The Community Hospital will serve the districts of Bushenyi, Sheema, Rubirizi, Buhweju, Mitooma
Munyamugisha is upgrading from a Medical Centre to an 88-Bed General Hospital (48 Medical + 40 Surgical + 16 Maternity + 6 NICU Incubators) — community-owned, professionally run, and built to Ugandan Ministry of Health 100-bed standards.
Why This Hospital?
Why Now?
For years, families in Greater Bushenyi have faced two painful realities:
1. They travel far to stay alive. A farmer in Buhweju spends UGX 80,000 every month to go to Mbarara for blood pressure drugs. A mother in Mitooma hires a car for UGX 300,000 at 2am because the nearest theatre is full. Distance kills.
2. Our facilities were built for yesterday’s diseases. Our Health Centre IVs were built for malaria and pneumonia. Today our wards are full of hypertension, diabetes, strokes, heart attacks, and boda-boda accidents. Greater Ankole has NO specialized clinic for NCDs and NO 24-hour emergency unit in any of its 5 districts.
Munyamugisha Community Hospital is the answer. Built for 2026-2035, and beyond

The Gap We Are Closing
A. The Ncd Crisis - No Clinic Exists:
Bushenyi District alone recorded a 181% rise in hypertension (4,200 to 11,800 cases) and 210% rise in diabetes between 2019-2024. At MCMC, 1 in 3 adults over 35 has high blood pressure.
Yet care is given on a general OPD bench — no counselling, no eye/foot screening, no drug follow-up. 67% of stroke patients referred to Mbarara had stopped treatment because of distance and cost.
People are getting amputated and stroked at 45 for diseases we can prevent.
B. The Emergency Crisis - No Unit Exists:
The Kasese-Mbarara highway through Rubirizi and Sheema brings 8-12 major trauma cases per week.
Our district has no resuscitation beds, no 24hr triage, no defibrillator. OPD closes at 5pm. At night, accident victims and mothers bleeding after delivery wait for a nurse to be called.
MOH Audit 2023 showed 41% of deaths in our region were due to delayed care in the first 60 minutes — the Golden Hour. This is preventable.
Our Solution: The First Two Specialized Units In The Region
1. THE FIRST SPECIALIZED NCD CLINIC IN GREATER BUSHENYI
Located on 2nd Floor Building C with its own 1:12 ramp access for elderly patients, this is not a table in OPD. It is a full clinic with 3 Consultation Rooms, Counselling Room, NCD Pharmacy with cold chain, ECG, HbA1c and foot-care station, and a digital registry that tracks patients.
It will provide daily clinics for Hypertension, Diabetes, Asthma, Sickle Cell and Epilepsy, prevent complications through eye, kidney and foot screening, and run outreaches to all 5 districts. Impact: 24,000 NCD patients will get local, affordable care per year, with zero travel to Mbarara for refills.
2. THE FIRST SPECIALIZED 24-HOUR EMERGENCY & CASUALTY UNIT IN GREATER ANKOLE
Located at the TOP North of our Site Master Plan, next to the Main Gate on Nyamiko-Rwenjeru Road for fastest ambulance access. This 100sqm unit will be open 24/7 with Triage Bay, 2 Resuscitation Beds with piped oxygen/suction, 4 Observation Beds, Minor Procedure Room and Decontamination Area. It connects via 2.5m covered walkways to Theatre 2, HDU 6-bed, Radiology (X-ray & Ultrasound) and Lab in under 30 seconds.
It introduces true Red-Yellow-Green triage for the first time. Impact: 6,000 emergencies per year will receive care within 10 minutes of arrival, cutting deaths from postpartum hemorrhage, road accidents and acute asthma by over 50%.
The Hospital Design: Approved Site Master Plan
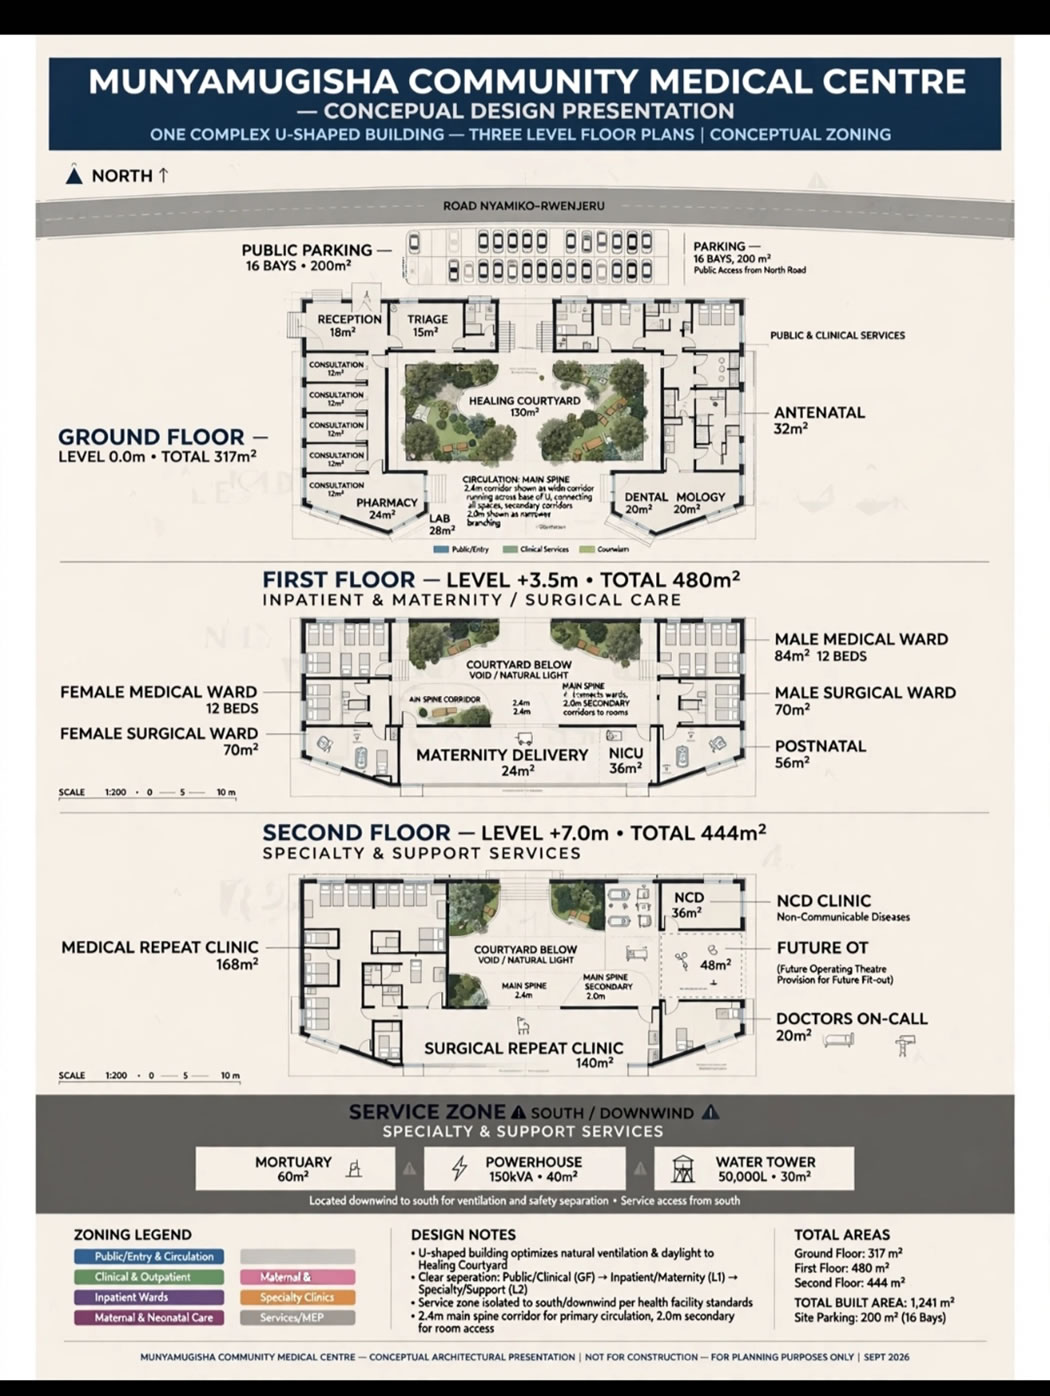
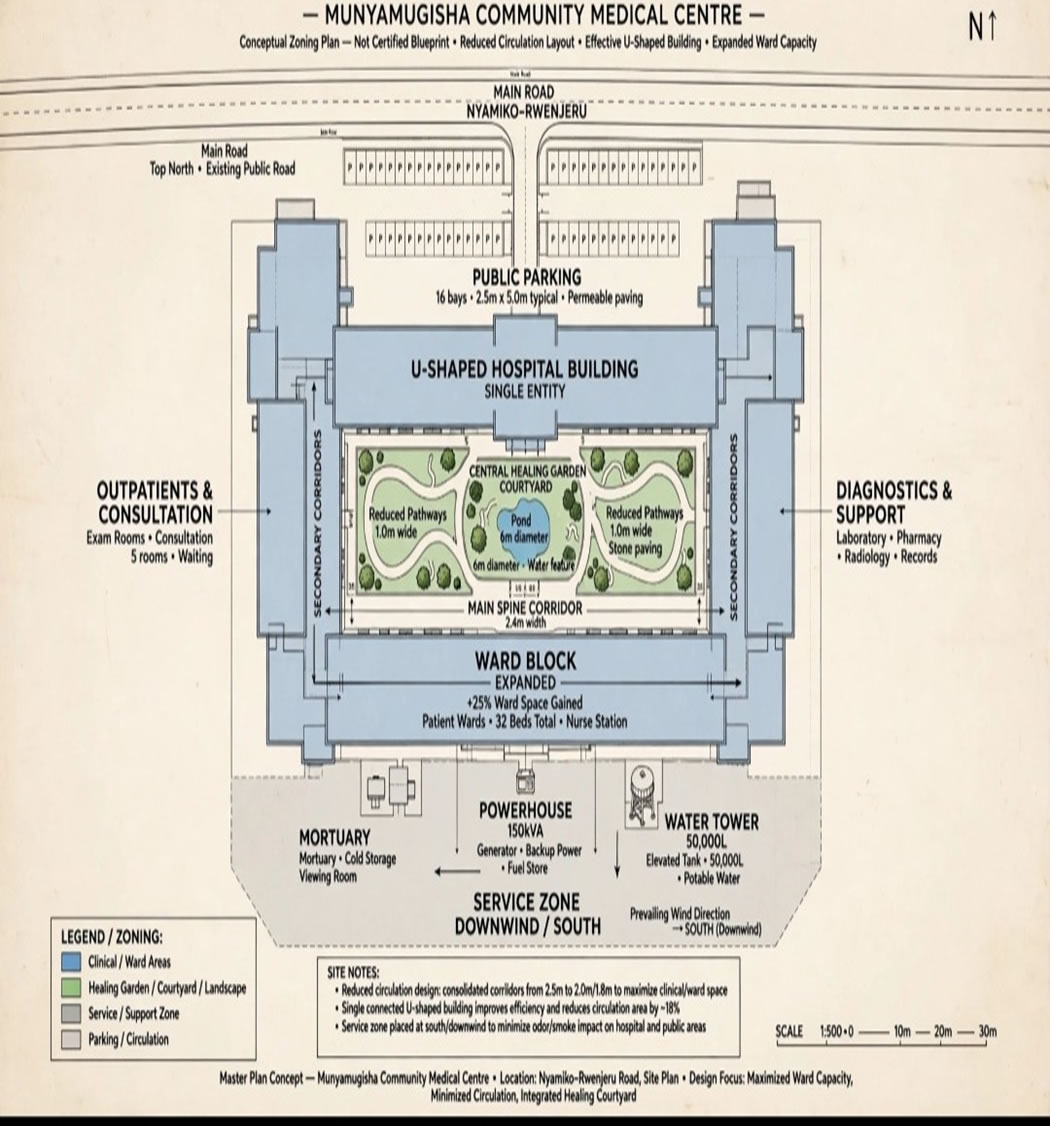
Our design converts the existing U-Shape plan into a modern hospital that respects infection control and patient dignity:
NORTH (Road Side): Main Gate, Triage, Public Parking 16 bays, OPD, Emergency Unit
CENTRAL U-SHAPE: Clinical core with 2.5m wide covered walkways for trolley flow and a Healing Courtyard Garden inside the U for recovery
SOUTH (Downwind): Power House 150KVA + 20KW Solar Hybrid, Water Storage 50,000L, Waste Management and Mortuary – safely >50m from wards
Floor Plan:
Ground Floor: Admin, OPD, Dental & Eye, Main Lab, Diagnostic Lab, Antenatal.
First Floor (68 Beds): Female Medical 12 + Male Medical 12 = 24, Female Surgical 10 + Male Surgical 10 = 20, Maternity 16 + Postnatal 8 + Delivery + NICU 6 incubators. Each wing has Central Nurse Station, Sluice 8sqm, Clean Utility 10sqm.
Second Floor (88 Beds Total): Medical 48 total, Surgical 40 total, and the NCD Clinic with future Operating Theatre shell.
All compliant with MOH: 900mm bed spacing, 1 toilet per 8 patients + PWD WC, ICT network for DHIS2, 150KVA power.

What Makes Us First Of Its Kind
We are not a private-for-profit hospital. We are community-owned, community-governed. Fees are capped, no one is turned away, surplus is reinvested. We are the referral hub for 28 lower facilities across 5 districts, with staff housing to retain 24-hour specialists.
Partner With Us - For National & International Stakeholders
- For Government of Uganda & DLGs: Help us achieve a functional General Hospital per 500,000 people, implement the NCD Strategy 2022-2030 and Emergency Medical Services Policy 2021, and decongest Mbarara RRH. We seek gazettement support and specialist secondment.
- For Donors & International Partners: Invest in a transparent, auditable model that delivers SDG 3.4 (reduce NCD deaths) and SDG 3.6 (halve road deaths) at community level. Phase 1 to gazettement: UGX 1.55B – 2.18B. Naming opportunities available for Wards and Units.
- For Diaspora & Greater Ankole Community: This is your home hospital. Sponsor a bed (UGX 2.5M), a NICU incubator (UGX 15M), a mother’s delivery kit (UGX 50k), or a staff house.
Needs Now:
– Equipping NCD Clinic: BP machines, Glucometers, HbA1c, ECG, Fundoscope
– Equipping Emergency Unit: Resuscitation beds, Defibrillator, Monitors, Oxygen concentrators
– Building: Emergency Unit + NCD Clinic + Theatre 2 + HDU + Radiology